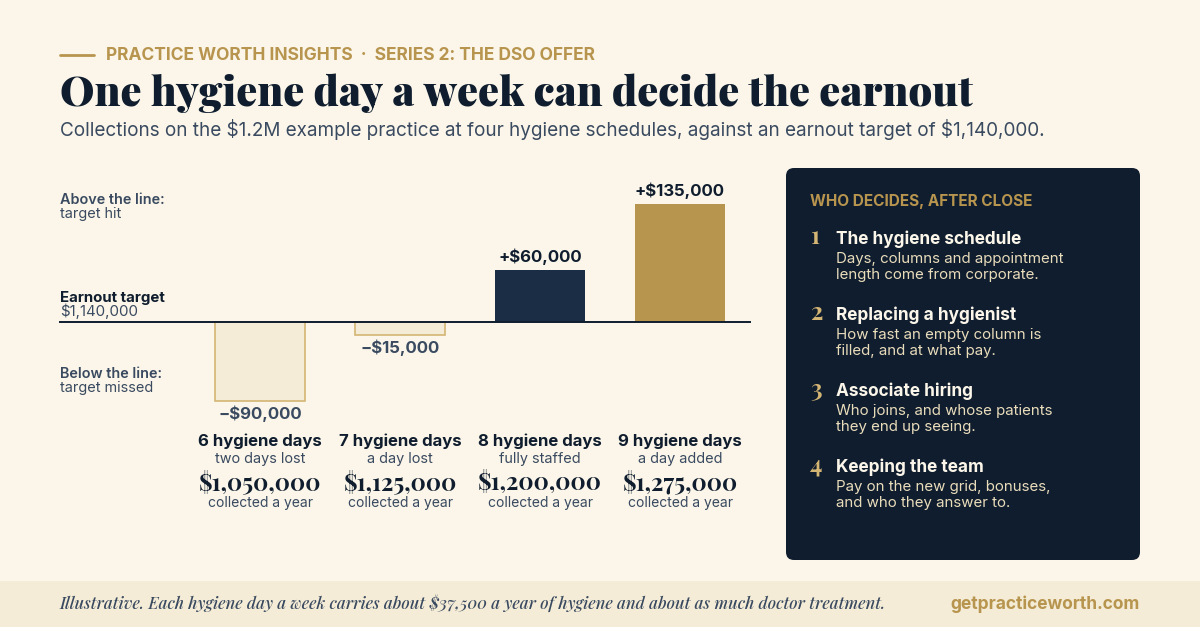
Hitting an Earnout With a Team You No Longer Run
Your earnout depends on production, and after the sale the DSO decides the hygiene schedule, how fast a hygienist who leaves is replaced, and which associates are hired. How one hygiene day a week can decide the example earnout, and the staffing terms to get in writing before you sign.
Read article →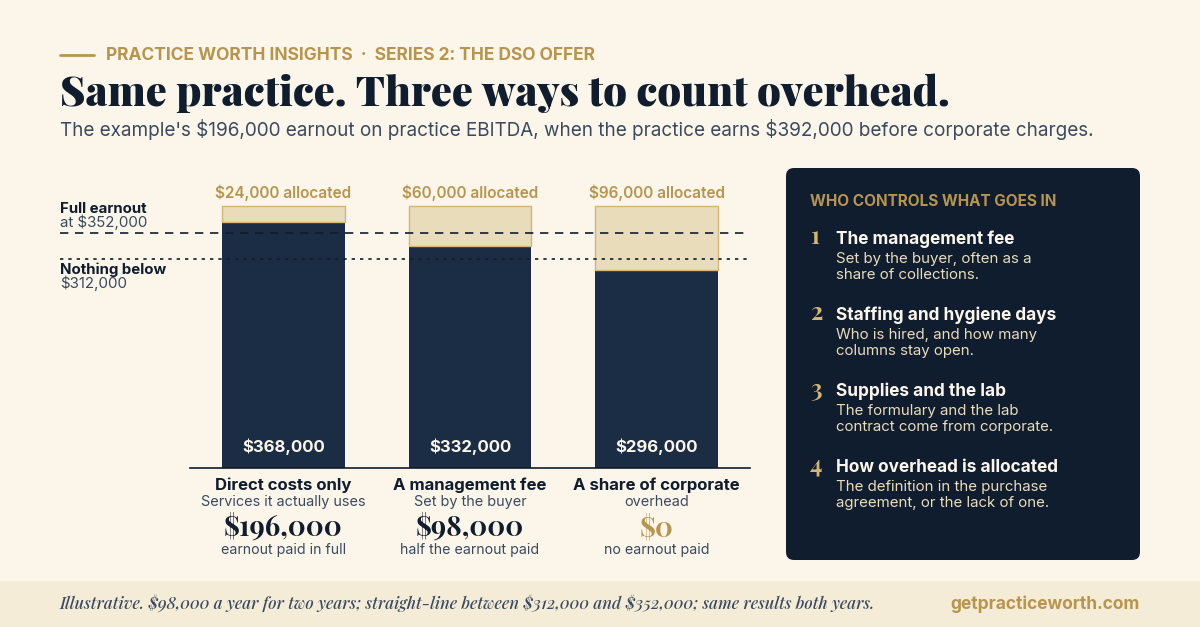
Earnouts: Who Controls the Number You Get Paid On
An earnout is a bet on a number the buyer controls after closing. Which metric it is paid on, how the same practice can earn the full $196,000, half of it, or nothing depending only on how overhead is allocated, the clawback and acceleration terms to ask for, and the trade that turns an earnout into money you can count on.
Read article →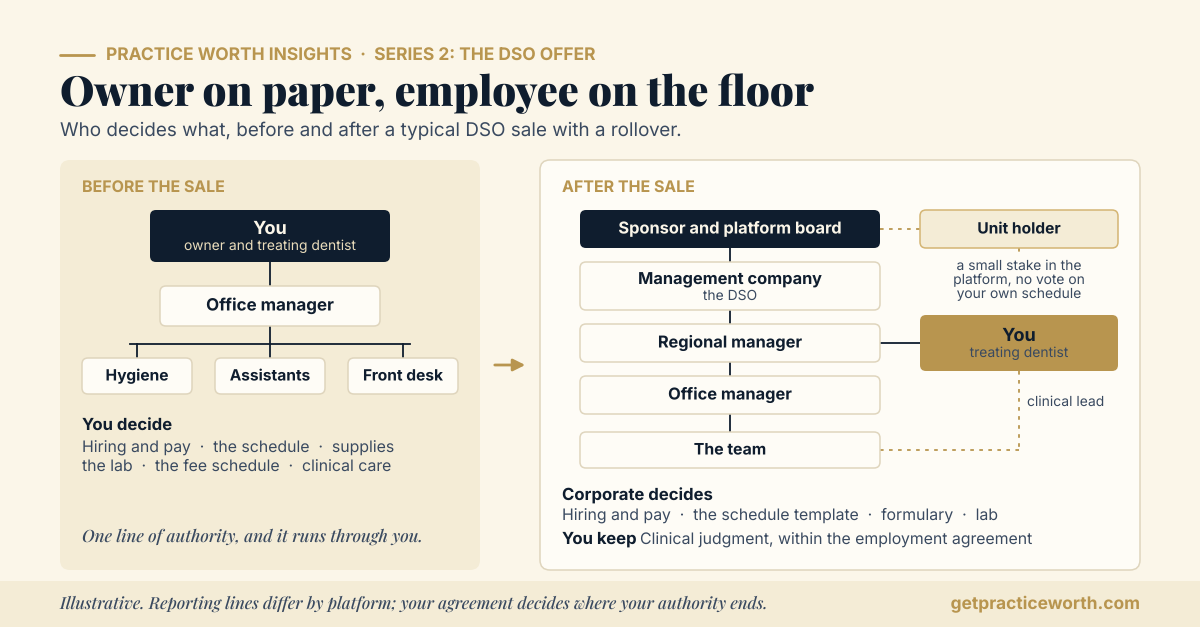
Owner on Paper, Employee on the Floor
After a sale with a rollover, you own a piece of the platform and answer to a regional manager. The mixed message your team hears, where your authority actually ends, how to advocate for the team inside a structure you do not control, and how to protect the culture the buyer paid for.
Read article →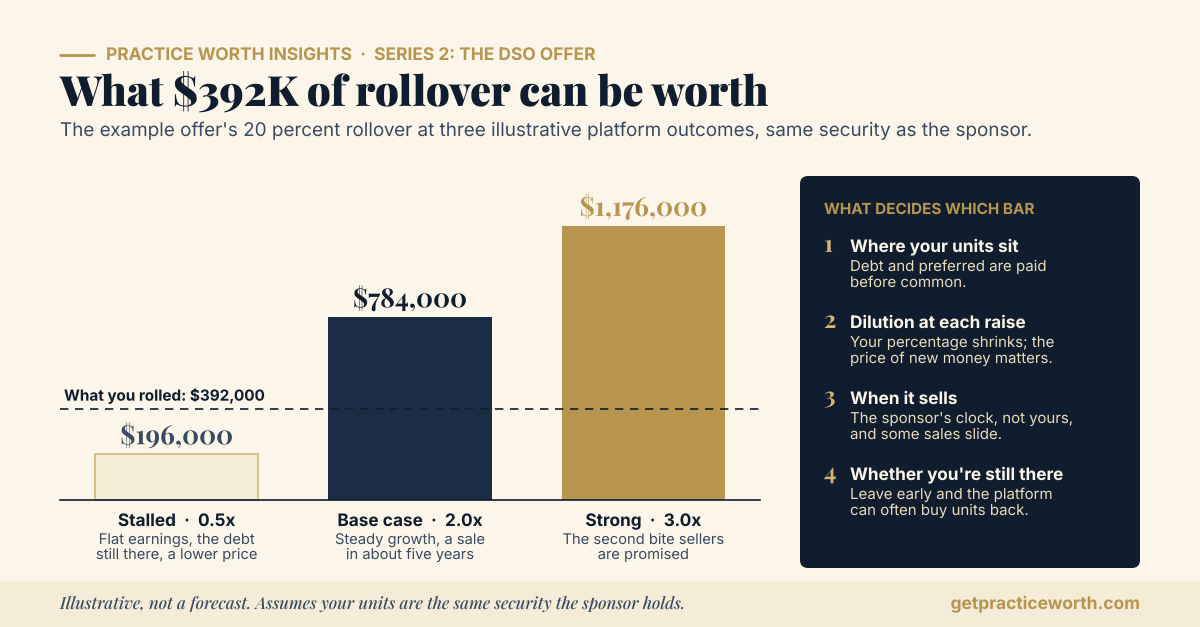
Rollover Equity and the Second Bite
Rolling 20 to 30 percent into the platform is where DSO deals are won and lost. What the example offer’s $392,000 of rollover can be worth if the platform stalls, grows, or sells well, why where your units sit in the stack can matter more than the sale price, and the questions to ask before you roll.
Read article →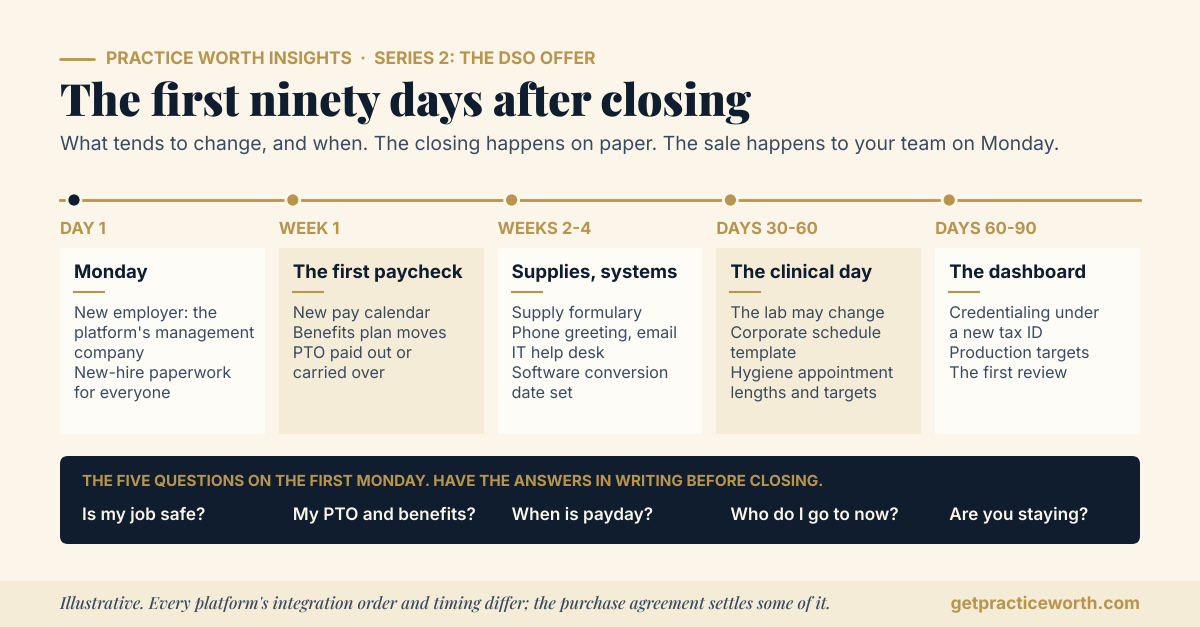
What Changes on the Monday After Closing
The closing happens on paper. The sale happens to your team on Monday. Payroll and benefits under a new employer, the supply formulary, the lab you may not keep, the schedule template from corporate, and credentialing, in roughly the order they arrive, plus the five questions your team will ask in week one.
Read article →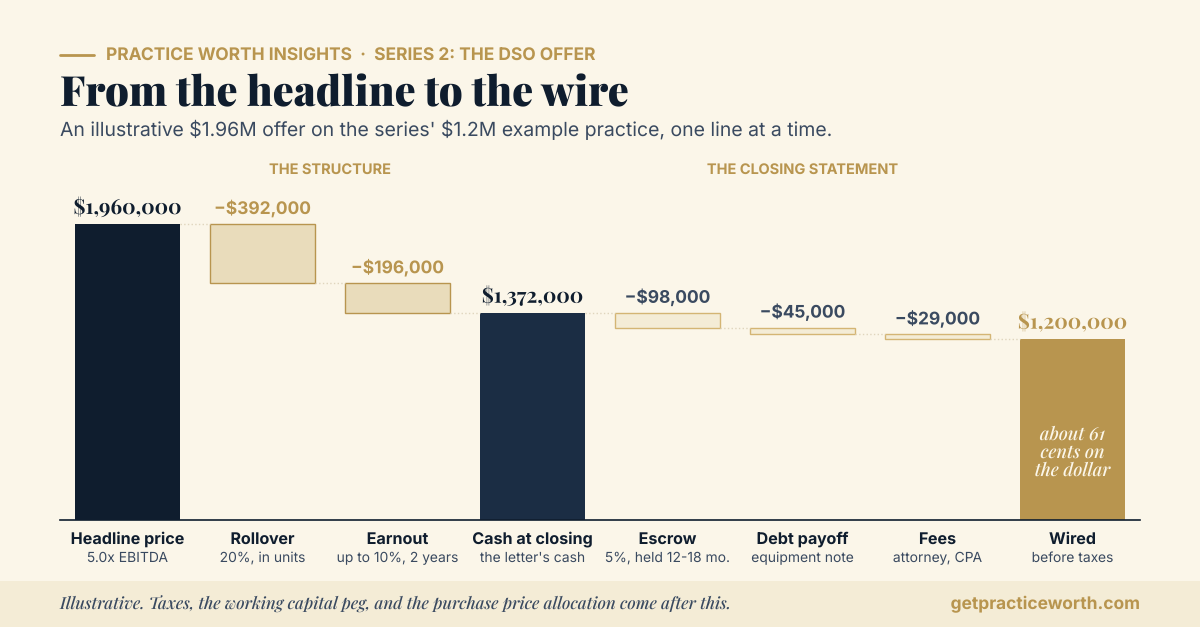
The Multiple They Quote and the Check You Get
A $1.96M headline can be about $1.2M on the wire at closing. The walk from the price in the letter to the cash that reaches your account: rollover and earnout, escrow, debt payoff and fees, then the working capital peg and taxes, and two offers with the same headline that land $588K apart.
Read article →
The Employment Terms Buried in the LOI
The financial terms get argued for weeks. Your job after closing gets one sentence in the letter of intent. Three ways to be paid for the same $900K of production and what each one takes home, the schedule template you inherit, the term and the cost of leaving early, and how to read the clinical control clause.
Read article →
Anatomy of a DSO Letter of Intent
The letter of intent is short, mostly non-binding, and written by the buyer’s lawyer. What each paragraph is doing on an illustrative letter for the series’ example practice: the price as a formula, the structure sentence that matters more than the headline, the exclusivity clause that binds only you, and the four things most letters leave out.
Read article →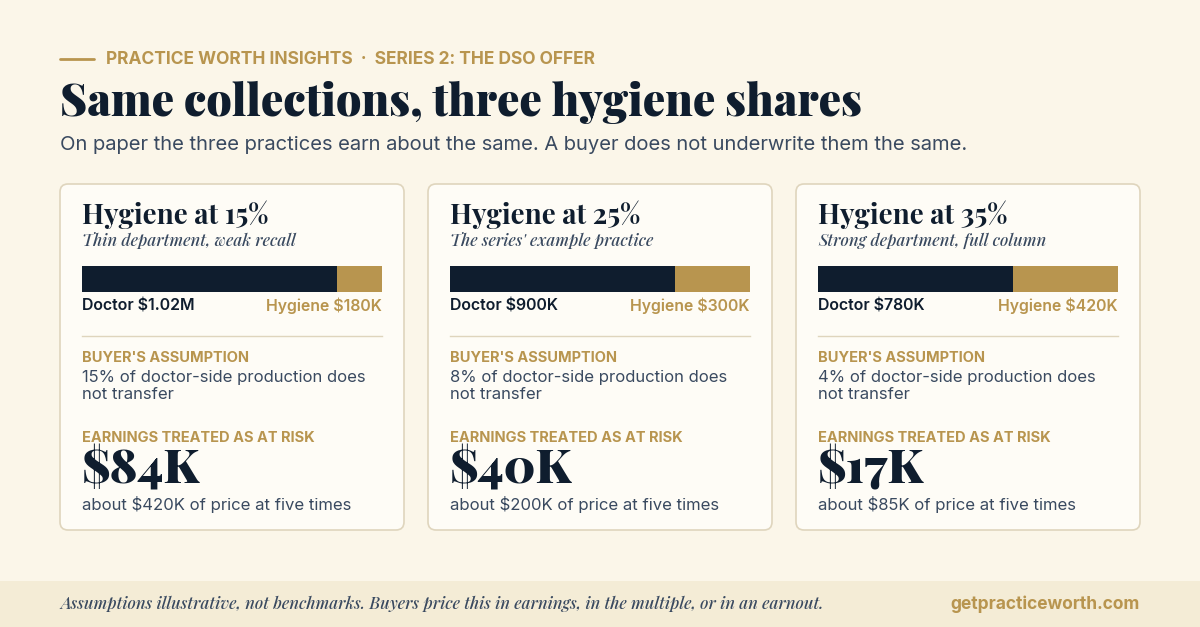
The Provider and Hygiene Numbers a DSO Will Rebuild
The financials tell a buyer what the practice earned. The provider and hygiene reports tell them how much of it will still be there after you are not. Why hygiene gets its own model, how much walks out the door with the owner, the active-patient count to settle before they define it for you, and recare as an earnings input. The same $1.2M practice, underwritten three ways.
Read article →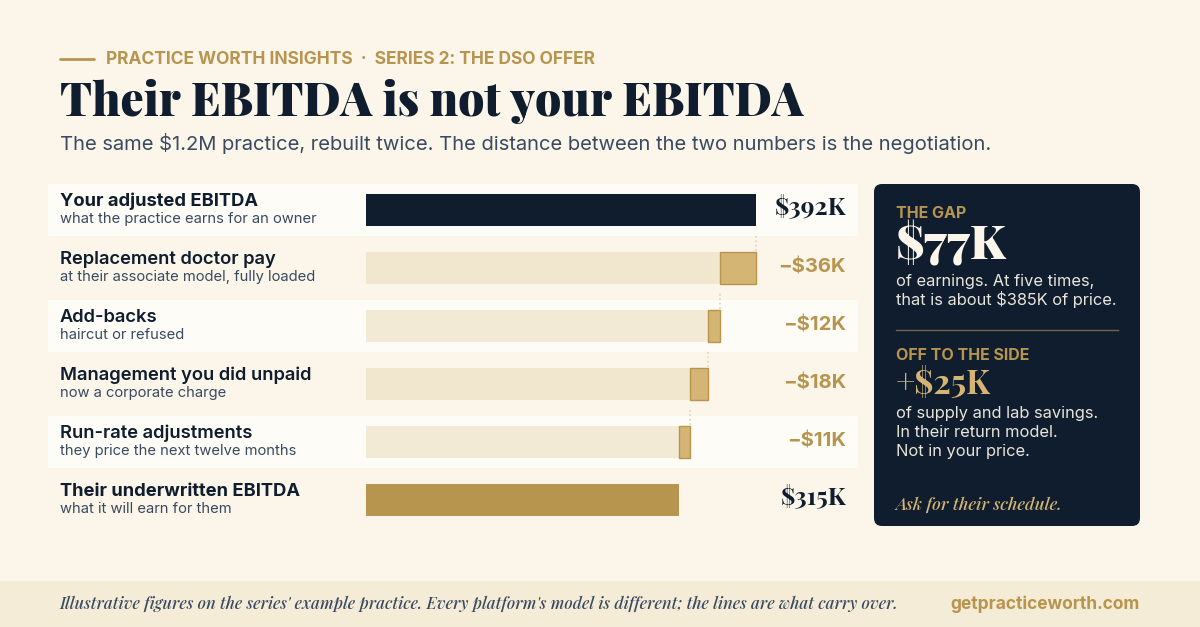
Why the DSO’s EBITDA Is Not Your EBITDA
You rebuilt your earnings the way a buyer would. Then the buyer rebuilt them again, with different assumptions, and did not show you the work. The four lines where the two numbers separate on the series’ example practice, from $392K to $315K, what settles each one, and why the first thing to ask for is their schedule and not their price.
Read article →
What to Tell Your Team When a DSO Calls, and When
The rumor that leaks in week one costs more than the negotiation. Confidentiality is a staffing decision, because the hygienist who hears first is the one who updates her resume, and the buyer's diligence prices the turnover. The three circles of who learns what, the answer for when they ask directly, and why your retention conversations come before the buyer's.
Read article →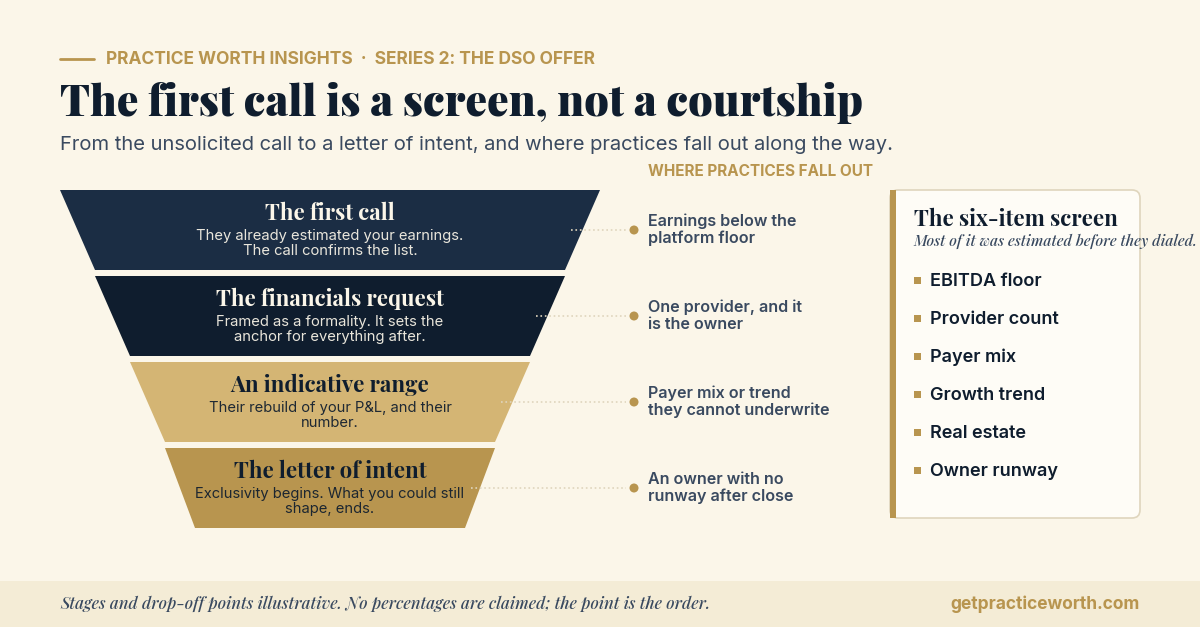
What a DSO Is Actually Screening For on the First Call
The first conversation is a screen, not a courtship. The six things the caller is checking, most of them estimated before the phone rang; why the P&L should not go out before you know your own number; the four questions to ask them; and why the unsolicited call is leverage only if you have a number to hold. Week one of a new series on the DSO offer.
Read article →
Getting Buyer-Ready Operationally Before You List
Diligence is not an interrogation, it is a records request, and the practices that struggle with it are the undocumented ones. The active-patient count with a definition attached, the recare rate pulled from the PMS, the SOPs that prove the practice runs itself, and the team a buyer inherits. A checklist to start working now, one item a week.
Read article →
The 24-Month Runway: What to Fix Now to Maximize Your Number
A buyer pays for the trailing twelve months, and most of the moves that raise a practice's value need a year or more to live there. The value levers sequenced over a real timeline, why a dollar of adjusted EBITDA returns $4.50 to $5.50 at closing, and why the slowest levers have to start first. The final piece in the twelve-week series.
Read article →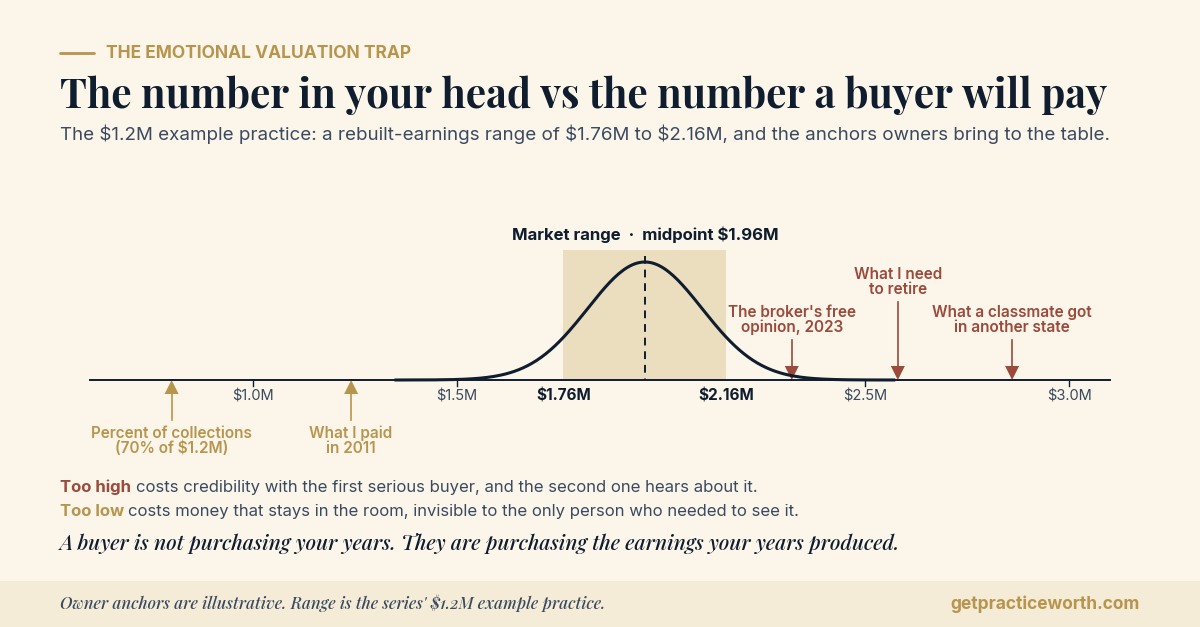
The Emotional Valuation Trap
Long before a sale, an owner is usually carrying a number that came from the years, a classmate, or a broker's old opinion. Too high costs credibility with the first serious buyer. Too low costs money that stays in the room, invisible to the only person who needed to see it. Why a documented outside number protects you in both directions.
Read article →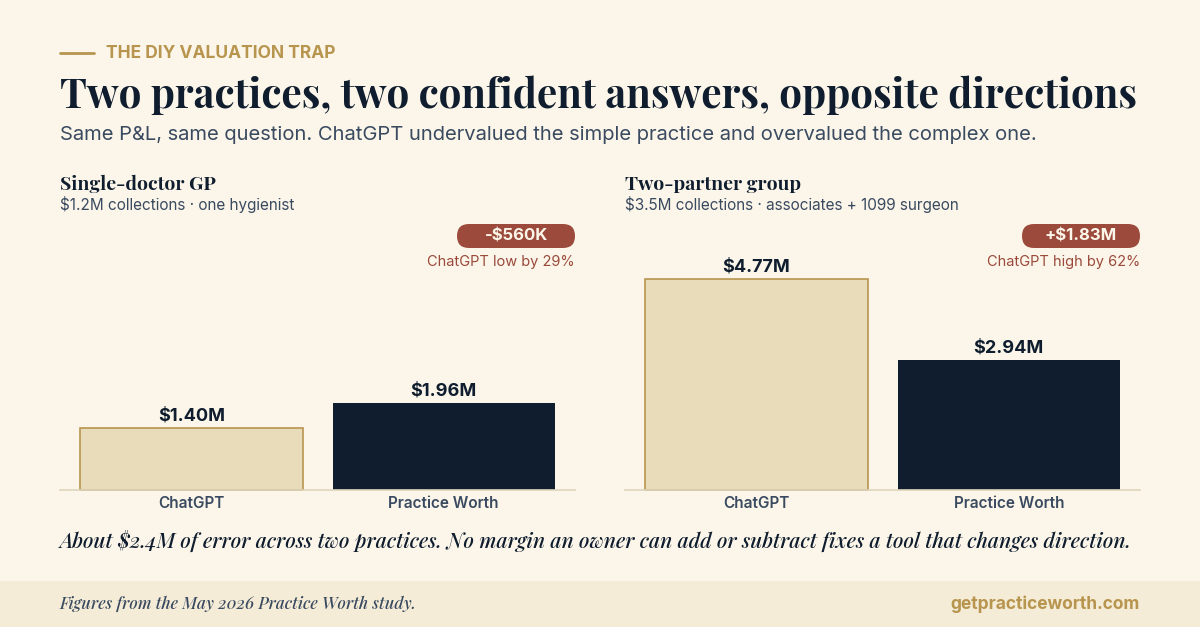
The DIY Valuation Trap
A rule of thumb, a free calculator, and ChatGPT all hand you a specific number in under a minute, and none of them tells you how far off it is or which way. In our two-practice test ChatGPT ran $560K low on the simple practice and $1.83M high on the complex one. Why a confident wrong number is the expensive kind, and the step every DIY route skips.
Read article →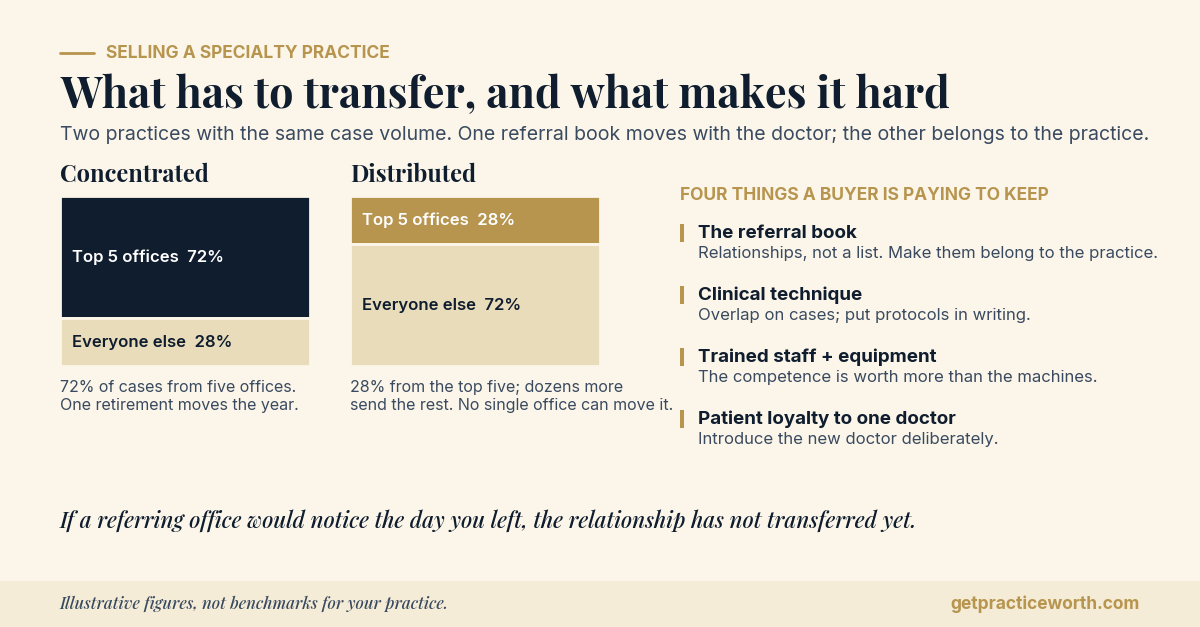
Specialty Workflows That Affect Transferability
A specialty practice lives in referral relationships, clinical routines, a trained team, and families who chose a doctor by name. A buyer is paying for all of that to survive the handoff, and whether it does is mostly decided a year before the sale. What to document, widen, and settle before you sign.
Read article →
Why Perio, OMS, and Pedo Don’t Value Like a GP
Percent-of-collections shorthand was built for general dentistry. A specialist inherits it by default and it is the wrong tool: the earnings base differs by specialty, the buyer pool is narrower, and referral and producer dependence get underwritten. Start with earnings, not collections, and treat the multiple as the second conversation.
Read article →
Staying On After You Sell
In most sales you do not leave at closing. A private buyer often wants six to twelve months; a group buyer frequently wants one to two years. The financial terms get argued over for weeks and the employment terms arrive at the end, as a form. They deserve the same attention, because the transition is the part you actually live in.
Read article →
Headline Price vs. What You Actually Pocket
A $1,960,000 headline splits into cash at close, rollover equity, and an earnout, and only the first one is money on the day you sign. Two offers carrying that identical sticker can differ by $588,000 in what actually lands in the account. Structure is a risk transfer, and it is negotiable.
Read article →
The Capacity You Don’t Know You’re Selling
Most practices hold more capacity than their owners realize: chairs producing on roughly 70% of their available hours, treatment diagnosed but never scheduled, referral slips walking demand out the door. A buyer sees built-in growth. The owner who finds it first, and documents it, is the one who gets paid for it.
Read article →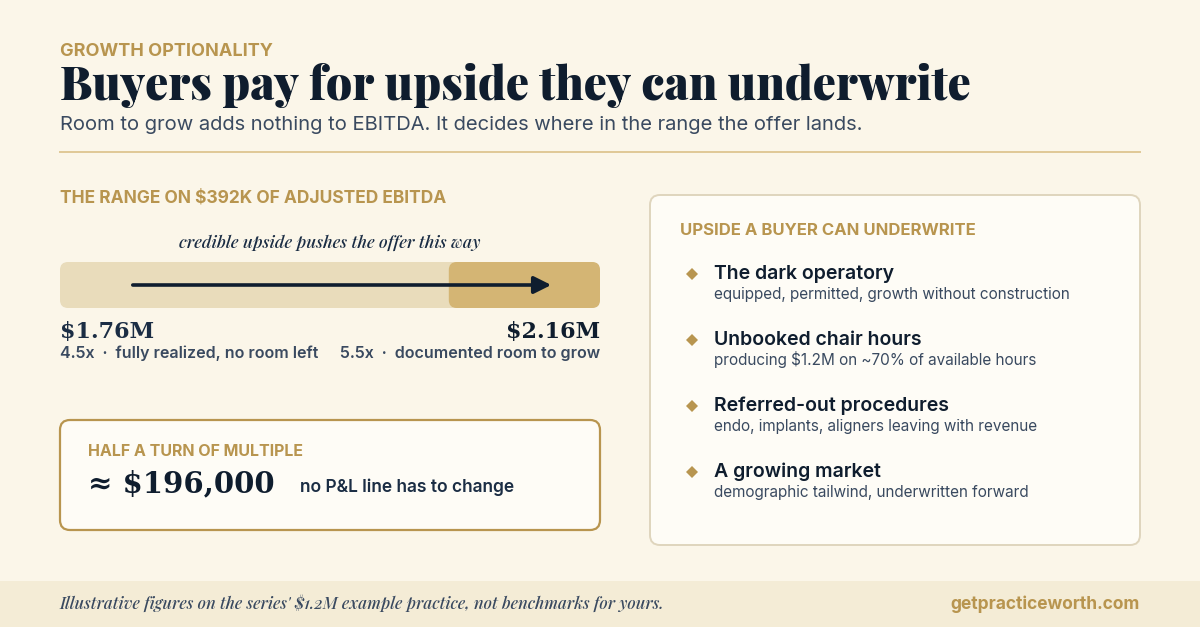
Buyers Pay for Upside: How Growth Optionality Is Priced
A buyer will not add hypothetical earnings to your EBITDA, but credible room to grow decides where in the range the offer lands. Unused operatories, unbooked chair hours, referred-out procedures, and a growing market, priced the way a buyer's model prices them, and why undocumented upside is worth zero.
Read article →
Lease, Location, and a Team That Stays
Before a buyer commits, they underwrite three things that never appear on a P&L: the lease and whether it transfers, the market the practice draws from, and the people who decide whether patients stay through a sale. Each one can be worked in the year or two before a listing.
Read article →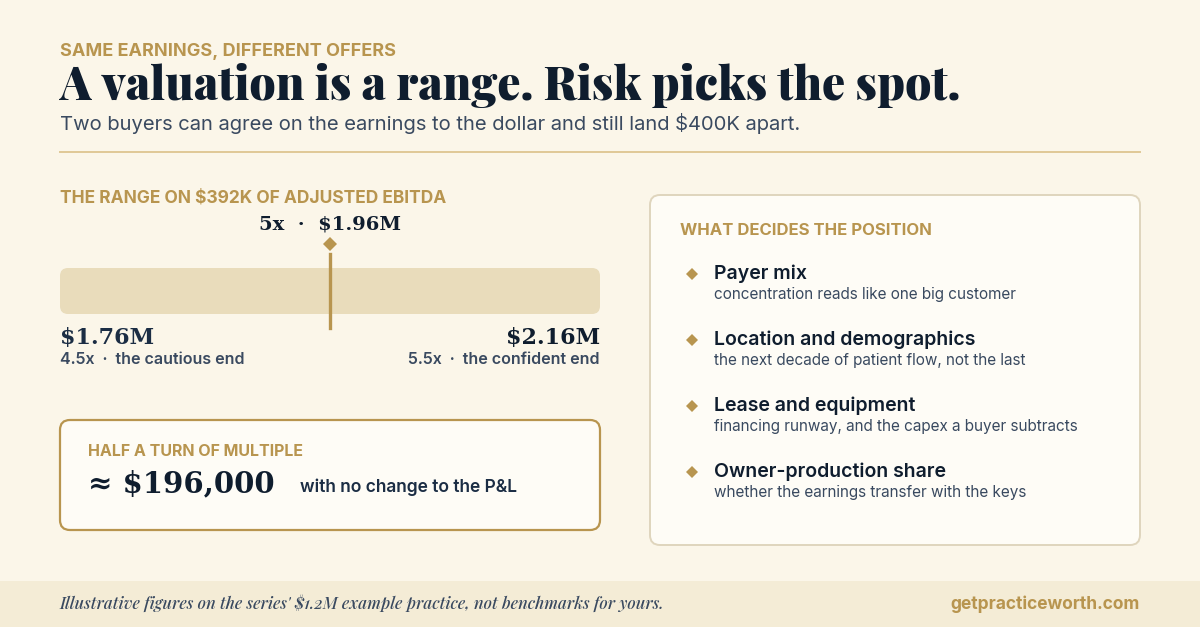
The Risk Factors That Move a Buyer’s Offer Within Your Range
A valuation is a range, not a number, and risk decides where in it an offer lands. On the example practice, half a turn of multiple is about $196,000 without a single P&L line changing. Payer mix, location, lease security, equipment, and owner-production share, read the way a buyer reads them.
Read article →
The Hygiene Department Buyers Pay a Premium For
A buyer can tell a hygiene engine from a leak in ten minutes with the schedule. Recare that runs itself, chairs that stay full, a real perio program instead of a prophy mill, and the hygienists whose tenure carries patients across a sale.
Read article →
What Your Hygiene Department Does to EBITDA
Owners read hygiene as a cost. Buyers read it as the most durable earnings in the building, the closest thing dentistry has to recurring revenue. The three-times-wages health check, the $75K capacity leak, and what a systematized hygiene engine does to the price.
Read article →
When Is a Practice “Big Enough” for a DSO?
Group buyers screen for provider count, EBITDA scale, and a recare system that runs itself, then look for the one thing that caps every offer: a practice that only runs with its founder. What DSO interest actually looks for, and what to do if an offer is already on your desk.
Read article →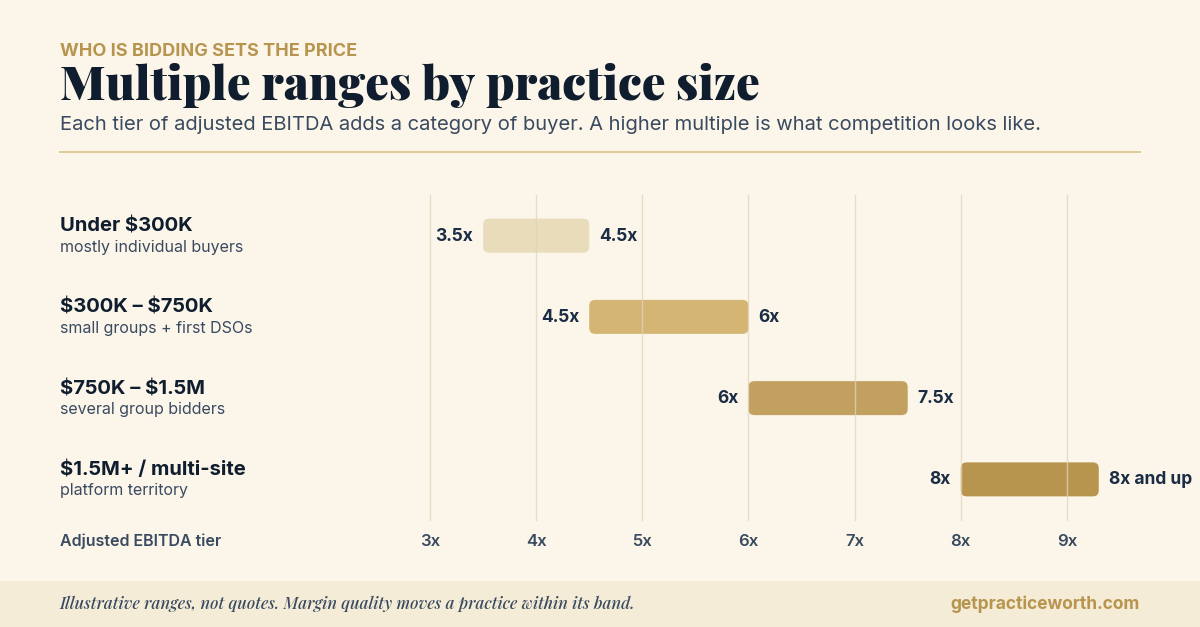
Why Two Practices Get Two Very Different Multiples
One practice sells at five times earnings, another at nearly seven, and neither number is wrong. How owner-operator and DSO buyers price differently, the EBITDA tiers where the buyer pool changes, and why one extra turn of the multiple is a full year of earnings at closing.
Read article →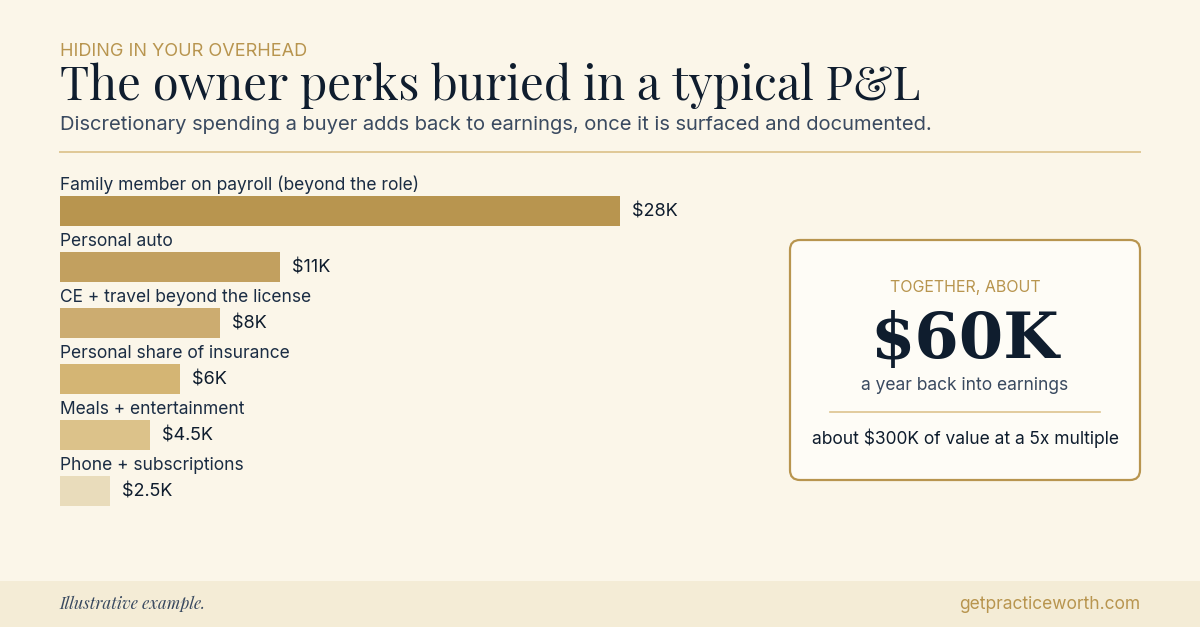
The Owner Perks Hiding in Your Overhead
The auto lease, the CE trip that was also a vacation, the family member on payroll. The discretionary spending buried in your P&L is not something to hide from a buyer; surfaced honestly and documented, it may be the easiest money in your entire valuation.
Read article →
Add-Backs That Hold Up, and the Ones That Get Laughed Out of Diligence
Every add-back is a claim, and documentation turns it into a deduction. Which adjustments buyers accept with a nod, which ones get rejected in diligence, and why one aggressive add-back can cost you more than the dollars involved.
Read article →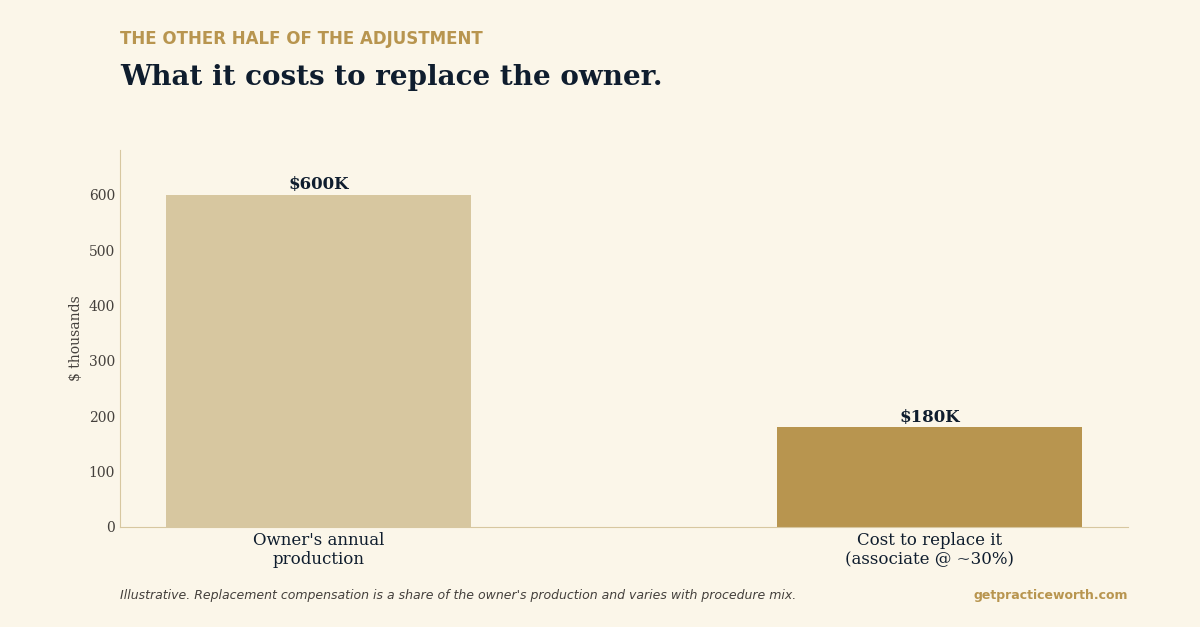
What a Replacement Dentist Really Costs
When you sell, someone still has to do the dentistry you do today, and that person gets paid at market rate. How associate compensation actually works, how procedure mix changes the math, and why this number may also be your own future paycheck.
Read article →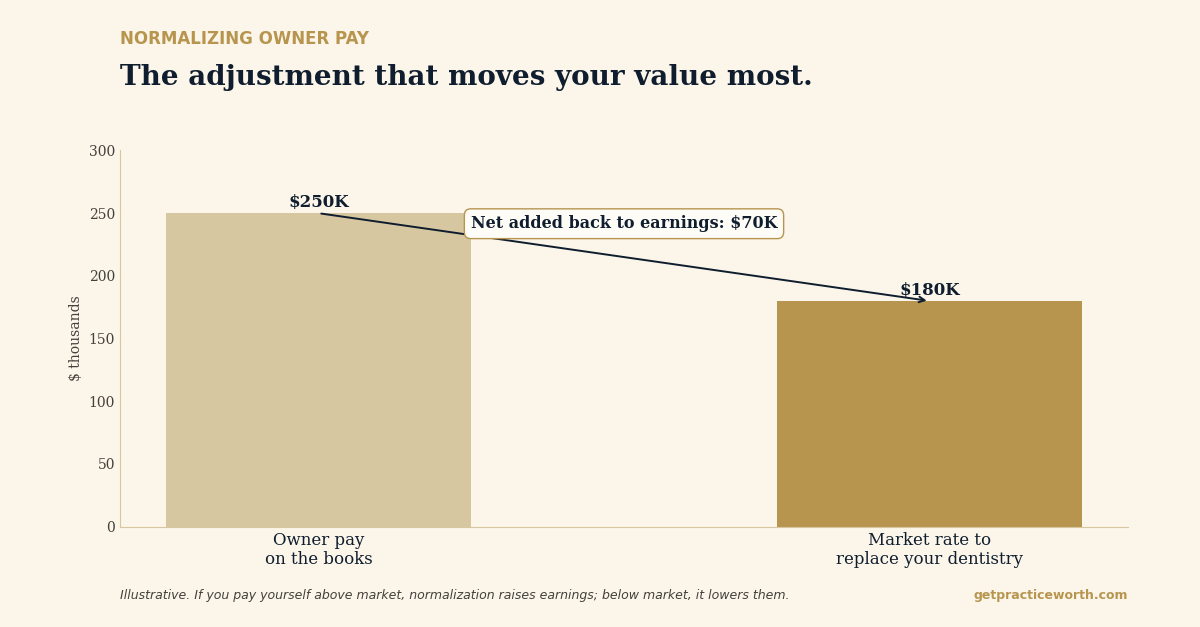
The Single Biggest Number in Your Valuation: Owner Compensation
One adjustment moves a valuation more than any other, and it is the one DIY tools most reliably get wrong. The two-step normalization of owner pay, why paying yourself below market can lower your value, and what happens with multiple providers.
Read article →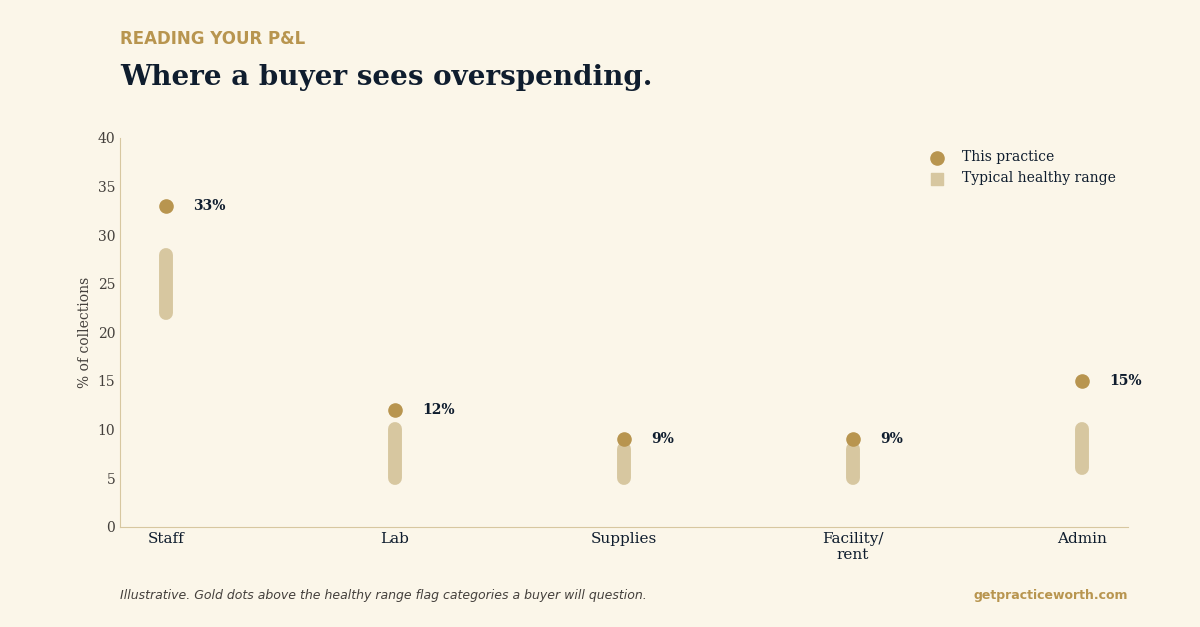
Reading Your P&L the Way a Buyer Does
Your profit-and-loss statement is a story about how your practice runs, and a buyer reads it that way. A chairside tour of the overhead categories, the staff-cost ratio buyers watch first, and why clean books translate into a higher, more defensible number.
Read article →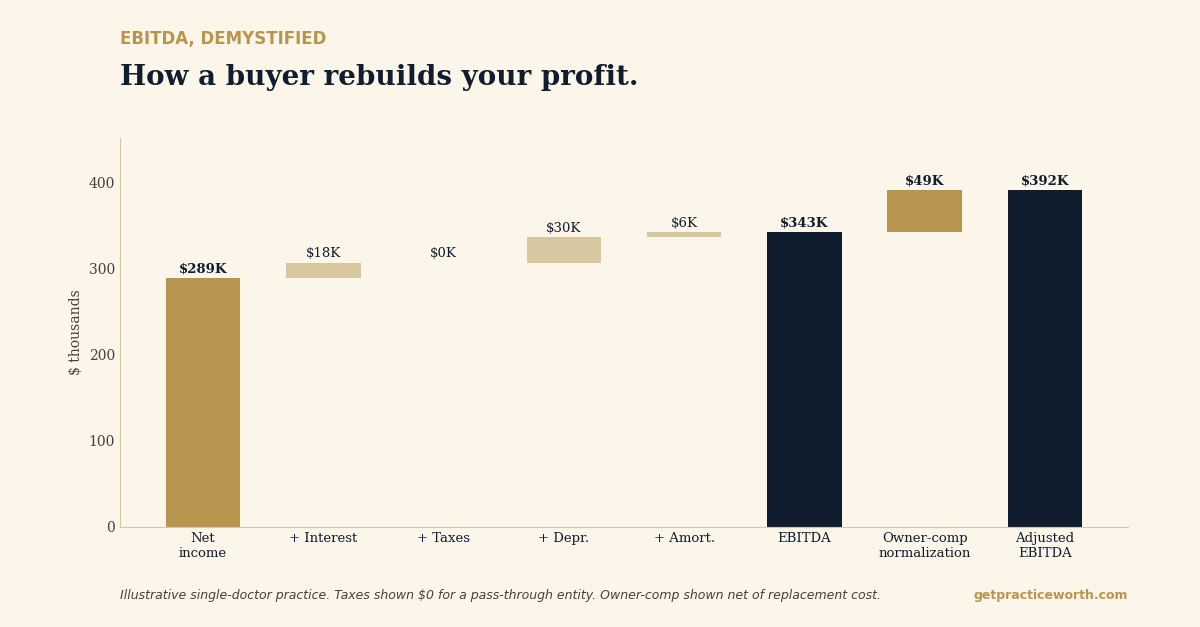
EBITDA for Dentists: How a Buyer Rebuilds Your Profit
Every serious buyer prices off adjusted EBITDA, and most owners have never had it explained plainly. The rebuild from reported net income to adjusted EBITDA, one line at a time, and why that number — not net income — is what an offer is built on.
Read article →
From Roll-Ups to Real Value: AI and the Future of Dental DSOs
Dave joins Ember AI’s Healthcare Intelligence Podcast to talk about where dental consolidation is headed, what separates real value from the hype, and how AI is reshaping the way practices are valued and bought.
Watch the episode →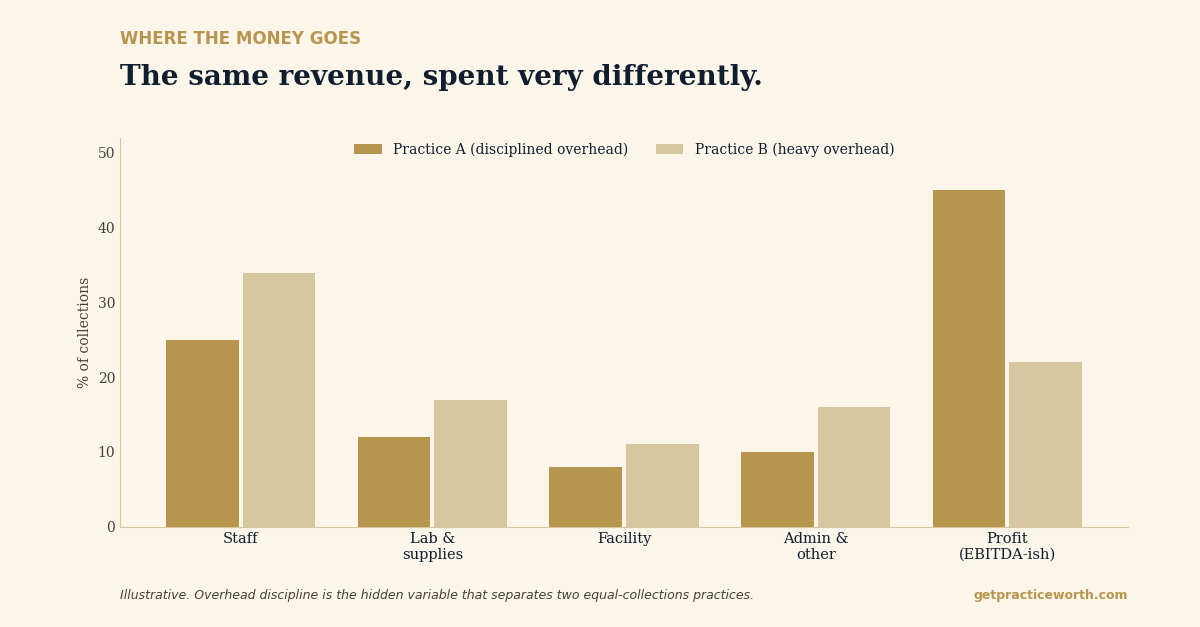
Same Collections, a Very Different Practice
Two practices can collect the same and be worth very different amounts. The operational reasons why: overhead discipline, a hygiene department that carries its weight, a team that stays, and what a buyer notices walking in the door.
Read article →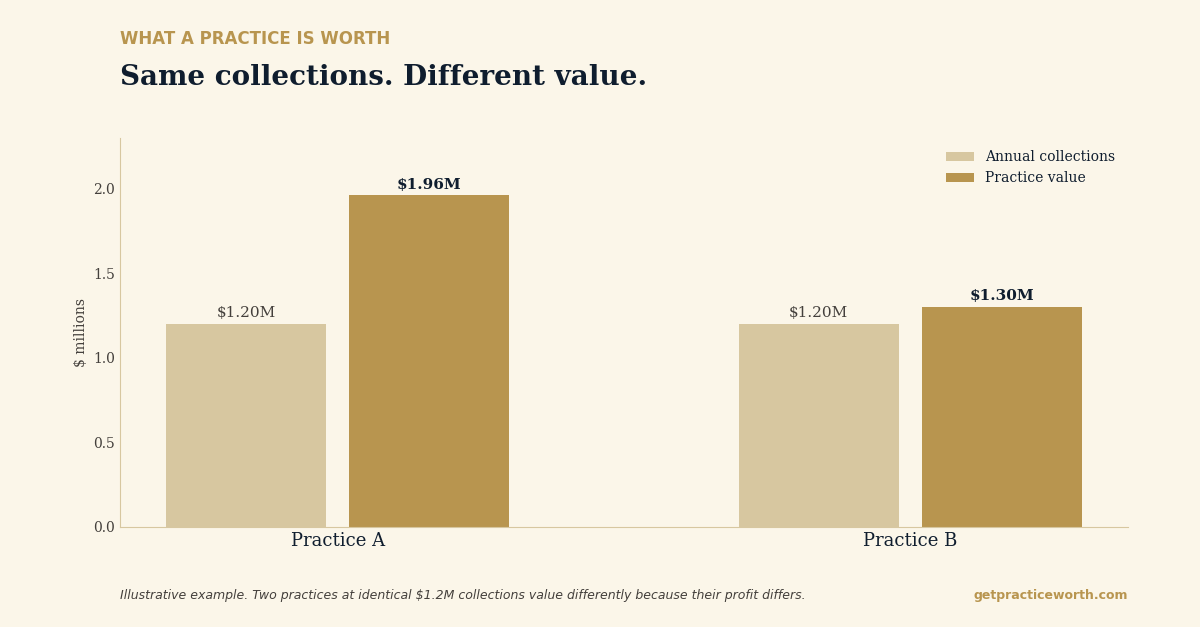
Your Practice Isn’t Worth a Percentage of Your Collections
The 70-to-80-percent-of-collections rule is wrong often enough to cost owners real money. Collections tell you how much came through the door, not how much stayed. What a buyer actually prices off, and why it can swing a value by six figures.
Read article →
The Most Valuable Part of Your Practice May Be the Part Your P&L Never Shows
Beyond the earnings, a buyer pays a premium for your hygiene program, a team that stays, patients who belong to the practice, and an office that runs without you. After two decades chairside, a hygienist and co-founder on the value most calculators can’t see.
Read article →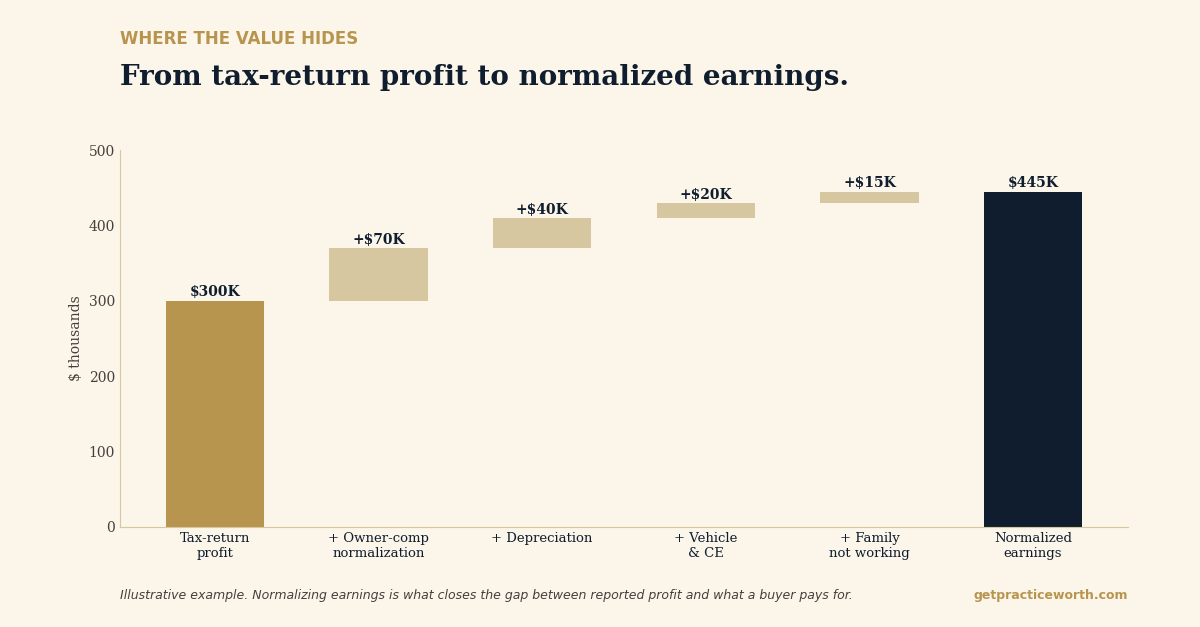
The Number on Your Tax Return Isn’t What Your Practice Is Worth
The honest number rarely matches the one on your tax return, and the gap is usually six figures. Where it hides: normalizing owner compensation and the legitimate add-backs a free calculator never sees.
Read article →
What Happened When We Asked ChatGPT to Value Two Dental Practices
We ran two real, anonymized dental practice P&Ls through ChatGPT and Practice Worth side by side. The errors added up to $2.4 million across two test cases, in opposite directions. A founder’s account of where general-purpose AI falls short on dental valuation, and what it means for any practice owner planning a sale.
Read article →More insights coming soon. Subscribe to be notified when new pieces publish.
In the news: Practice Worth Launches Dental Practice Valuation Platform · June 9, 2026.